Investment Capital's Bets on ABA

Investors have placed their bets on ABA’s tech stack. Whether those bets pay off depends on where providers place theirs.
Part Three of MissionViewpoint’s series: Where Capital Is Betting on ABA
This series began with a contradiction.
Reimbursement uncertainty has made ABA provider economics difficult to underwrite, and the largest providers keep growing without combining with one another.
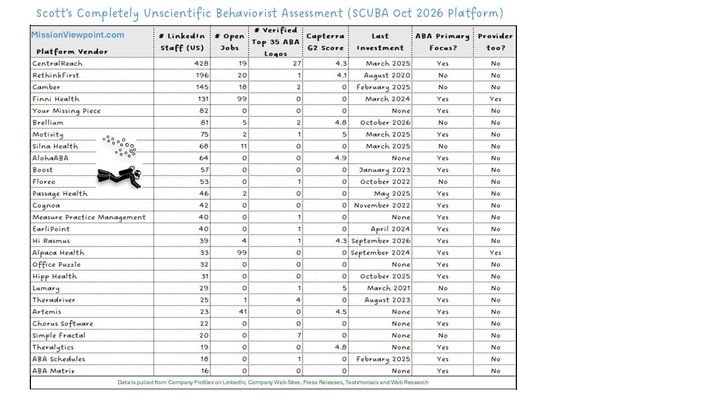
Yet this fall, Hi Rasmus announced a $50 million minority investment and Brellium raised another $23 million, following Motivity’s acquisition of Calmanac in May.
Part Two examined three ways technology companies are competing for enterprise spending: assembling a more complete platform, moving the clinical layer to a specialist, and adding capabilities alongside existing systems.
Each offers a different path to growth, but none produces a return until providers decide to spend money on it.
I closed that article with two questions: which capabilities become strategic enough to build, partner for, or acquire? And how much of the capital flowing into ABA technology companies will ultimately remain focused on ABA?
Both lead to a more fundamental question.
Investors and technology companies decide what platforms to fund, develop, or acquire.
Providers decide which capabilities to build themselves, which to license and operate with their own people, and which to outsource to vendors delivering completed work.
Those provider decisions determine whether the platform investments pay off.
The Provider’s Next Dollar
Return to the provider from Part Two. It operates fifty clinics across three states, a Medicaid plan is questioning its weekly treatment hours, and its systems cannot consistently produce the clinical evidence its clinicians believe exists.
It could hire analysts to connect its systems, license documentation review, outsource authorization and denial work, or evaluate a new clinical or practice management platform.
Each option represents a different allocation of the provider's resources and a different opportunity for technology companies and their investors.
AI is making those choices more interesting by changing what providers can reasonably develop themselves and what specialists can deliver economically.
Rent What Capital Is Improving
The strongest case for renting is a capability that a technology company can develop and improve across many customers: clinical platforms, documentation compliance review, or practice management.
A well-funded vendor can spread product development, security, maintenance, and support costs across its customer base. A provider building comparable software internally must justify those costs largely through its own operations.
Brellium illustrates the appeal of licensing specialized capabilities. Its technology reviews clinical documentation across existing systems, identifying potential deficiencies before they become denials, clawbacks, or audit findings.
Hi Rasmus represents a related opportunity: a clinical platform that can operate alongside multiple practice management systems.
Neither necessarily requires replacing the provider's core operational platform.
For investors, the opportunity is recurring revenue, expansion across enterprise accounts, and additional capabilities sold to existing customers. But adoption has to be practical. A capability that looks valuable in a demonstration and proves difficult to integrate may never move beyond a pilot.
And renting doesn't transfer responsibility for the result. When documentation review identifies a deficiency, the provider still needs people and processes to address it.
The decision also isn't permanent. If documentation review becomes a standard feature of practice management systems, a provider paying a specialist today may eventually find similar functionality included in software it already licenses.
The specialist then has to demonstrate why its additional capabilities justify another contract.
A capability can remain valuable even as the business selling it becomes less differentiated. That's an important risk for investors financing specialized technology companies.
Outsource the Outcomes Specialists Deliver at Scale
Outsourcing goes further. Rather than licensing software and assigning employees to operate it, the provider pays a vendor to deliver completed work: eligibility verified, authorizations tracked and renewed, denials resolved.
A specialist working across many organizations can develop processes, staffing models, and automation that an individual provider might struggle to replicate economically.
AI could make that advantage more significant. A vendor processing thousands of authorization requests can distribute automation costs across a large volume of transactions while concentrating its people on exceptions.
But providers have access to many of the same underlying AI technologies. A sufficiently capable internal team may automate portions of the work that previously justified outsourcing.
The advantage for specialists may increasingly come from combining automation, domain expertise, and accountability for completed outcomes rather than simply supplying people to perform administrative tasks.
That distinction matters to investors. A labor-intensive services business and a technology-enabled business that can grow transaction volume without proportionally increasing staffing have different economics.
Outsourcing also creates dependency. Vendors need reliable access to provider information and clean handoffs with internal operations. When something fails between systems, the provider remains accountable to the payor.
The decision isn't simply whether an outside organization can perform the work more cheaply. It's whether the vendor can deliver a better result without creating operational dependencies that outweigh the benefits.
Own What You Can't Afford to Lose
That leaves the work no single vendor is positioned to own.
Suppose our provider subscribes to documentation review, keeps its practice management system for scheduling and billing, and moves clinical work to a specialized platform.
Documentation review flags a session note that doesn't support the hours billed. The note lives in the clinical platform, the claim in the PM system, and the flag in a third.
Someone has to reconcile them, correct the underlying records where appropriate, and maintain the connections that make that possible next year.
In more mature enterprise software markets, systems integrators such as Accenture or PwC help organizations implement and connect complex technology environments. ABA has consultants, implementation specialists, and integration developers, but it hasn't developed a comparable independent systems integration ecosystem at scale.
That may reflect the economics of the market.
ABA's platforms are expanding into one another's territory, interfaces vary, and technology combinations that make sense today may look different two years from now. An independent integrator could spend much of its effort rebuilding what it previously developed.
That doesn't mean a viable services business can't emerge. But repeatability is difficult when each customer requires substantial customization and continuing maintenance. For now, much of that responsibility may remain with providers and their technology vendors.
The same problem appears when a provider changes systems.
Session notes, authorizations, claims, and timesheets can be essential evidence in responding to payor audits, clawbacks, and wage-and-hour claims. Preserving individual documents isn't always enough. The relationships between them matter.
Keeping a legacy practice management system running can preserve historical access, but it may mean paying for two systems, potentially for years. Providers I've spoken with describe receiving little or no meaningful discount from legacy vendors when they need only historical access.
Extracting that history into an archive the provider controls can offer a less expensive long-term alternative, provided it preserves the information and relationships needed to reconstruct the record.
The one thing a provider can't afford to lose is control over the connection between its own records.
That doesn't mean every provider needs its own data warehouse or a team of integration engineers.
It means retaining accountability for the integrity, accessibility, and portability of information, regardless of which vendors store or process it. The implementation can be developed internally, delivered by a specialist, or supported through managed services.
But the provider needs consistent definitions for authorized, scheduled, delivered, documented, and billed hours. It needs identifiers connecting the same client, clinician, and session across systems, and a way to preserve those relationships when applications change.
That foundation has value beyond reporting and audit preparation.
A provider that controls its connected information can adopt specialized capabilities, replace underperforming vendors, and evaluate new practice management platforms without treating every change as a complete rebuilding of its information environment.
It can also move functionality back into an existing platform when bundling makes economic sense.
Those options have financial value. They can reduce switching costs, improve negotiating leverage, and make future technology investments less risky.
In a market where the technology stack is still changing, the ability to change your mind may be one of the most valuable capabilities a provider can retain.
A vendor can help build and maintain that foundation. What the provider shouldn't surrender is control over its design and continued accessibility.
That puts an obligation on platforms hoping to move providers away from their legacy systems.
A challenger needs to own the migration, including the extraction, conversion, and validation of historical records, rather than handing the problem back to the provider as an implementation project.
And once the provider arrives, the platform needs to provide reliable access to its data and support connections to the other capabilities the provider uses. A platform that wins customers by promising an escape from legacy lock-in, then makes its own data difficult to retrieve or integrate, has simply built another walled garden.
The enterprise replacement bets discussed in Part Two may depend as much on meeting those expectations as on delivering better software.
AI Changes the Economics
AI introduces another complication into the build, rent, and outsource decisions. Much of the underlying technology is increasingly accessible to everyone.
A provider doesn't need to develop its own foundation model to create an application that identifies scheduling discrepancies, summarizes operational exceptions, or reconciles information across systems. It can license AI technology and develop the workflow around it.
That makes some internal development more practical than it was a few years ago.
It also creates pressure on specialized vendors. A company selling software for a narrow administrative task may find that providers, practice management platforms, or competing vendors can increasingly reproduce portions of its functionality.
Outsourcing companies face a related challenge. AI can improve their margins by reducing the labor required to deliver services, but it can also make those services easier for providers to perform internally.
The competitive advantage may shift toward reliable execution, integration, and accountability rather than access to the underlying technology.
There are limits. Building a prototype is not the same as operating a reliable production system. Security, validation, maintenance, and operational support remain significant costs.
But AI changes what is economical to build, rent, or outsource.
And it makes connected information more valuable.
A model reviewing clinical documentation without knowing what was authorized, delivered, or billed cannot independently establish whether the complete record supports reimbursement. With reliable access to those relationships, it can potentially answer much more consequential questions.
Models will improve, applications will change, and capabilities that command separate subscription fees today may eventually become standard features.
The provider's ability to connect its information is what allows it to benefit from those changes without repeatedly rebuilding the underlying infrastructure.
Will the Capital Stay Focused on ABA?
There's another question behind these investments: how much of the capital flowing into companies serving ABA will ultimately be spent developing capabilities for ABA?
Brellium illustrates the issue. Its documentation compliance technology addresses problems that extend beyond autism services. The company is pursuing opportunities across healthcare, where documentation quality and reimbursement exposure create similar demands.
For investors, a larger addressable market can make the business more attractive. But it also creates competing priorities.
A company serving several healthcare specialties must decide where to direct product development, implementation resources, and commercial investment. Features important to ABA providers may compete with opportunities serving larger markets.
The reverse is also possible. Expansion beyond ABA can finance better technology, stronger infrastructure, and more sophisticated automation that ABA customers benefit from without bearing the full development cost.
Specialization creates advantages. Understanding ABA's clinical workflows, authorization requirements, scheduling complexity, and reimbursement rules takes time. Those capabilities may be difficult for a general healthcare technology vendor to reproduce.
But specialization also limits the potential market. There are only so many large ABA providers, and companies seeking substantial growth may eventually expand into smaller organizations, adjacent specialties, or broader healthcare.
Neither strategy is inherently better for ABA providers.
Capital raised by a company serving ABA doesn't guarantee that ABA will remain its principal investment priority. Nor does expansion beyond ABA necessarily mean the company is becoming less valuable to its ABA customers.
The more useful question is whether its growth strategy continues strengthening the capabilities providers depend on.
Where the Next Bets Get Decided
The series began with what looked like a contradiction: capital reluctant to combine large ABA providers while investing heavily in selected ABA technology companies.
It isn't necessarily one.
The difficulty of evaluating provider reimbursement risk may help explain why consolidation among the largest organizations remains limited. Meanwhile, investors are financing technology companies that address some of the same operational problems without directly assuming responsibility for delivering care.
Those investments carry different risks. Technology companies remain exposed to provider budgets, reimbursement pressure, competition, and the challenge of turning promising capabilities into sustainable businesses.
Their returns depend on providers having both the financial capacity and the operational ability to adopt what they're selling.
AI is changing what providers can develop internally and what specialized vendors can deliver economically. Platforms are expanding their capabilities, potentially absorbing functions that once justified separate applications. And technology companies serving ABA may increasingly find their growth opportunities in other healthcare markets.
No one knows exactly which combination of technologies will prevail.
That uncertainty makes the ability to change direction valuable.
For providers, the allocation follows. Rent what capital is improving. Outsource the outcomes specialists can deliver at scale. Retain control over the evidence and architecture that allow those decisions to change.
For investors, the opportunity depends not simply on developing capabilities providers need, but on making them practical to adopt and valuable enough to keep.
That's where capital is betting on ABA. Its return depends on where providers bet theirs.
If this analysis is useful, you can subscribe to receive future SCUBA updates and related insights through the MissionViewpoint newsletter.